


Estimated reading time at 200 wpm: 7 minutes
This paper examines the contemporary nature of forensic psychiatry in the United Kingdom, arguing that the discipline has undergone a fundamental transformation over the past fifteen years. Through an analysis of daily practice, statutory frameworks, and professional competencies, this paper proposes that forensic psychiatry has evolved into a predominantly legal-administrative discipline wherein medical knowledge serves an instrumental rather than primary function.
Whether or not you agree our Fat Disclaimer applies
Introduction
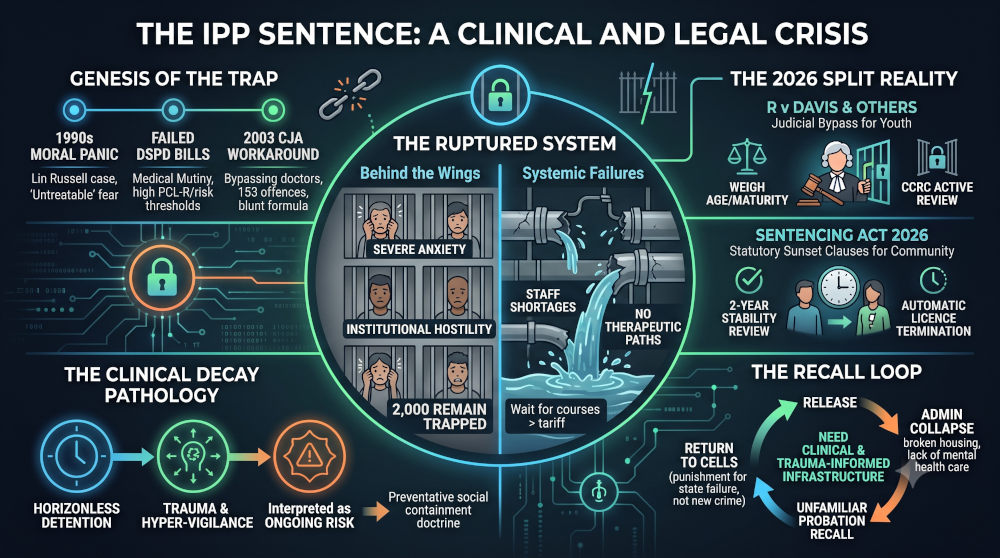
Since its poorly defined origins around 1808, psychiatry has struggled with questions of identity and purpose. This identity crisis becomes particularly acute in forensic psychiatry, where the intersection of mental health and law creates unique conceptual and practical challenges. The central thesis of this paper is deliberately provocative: that contemporary UK forensic psychiatry has become more a legal than a medical discipline, fundamentally altered by the mesh of statute, precedent, quasi-legislation and national guidance that now defines its practice.
The legal architecture of modern forensic psychiatry
The transformation of forensic psychiatry cannot be understood without examining the legal framework that now constitutes its operational reality. The Mental Health Act 1983 (as amended), the Mental Capacity Act 2005, their respective Codes of Practice, and the accumulated weight of case law from Winterwerp to Rooman have created more than external constraints on psychiatric practice. These legal instruments have become constitutive of the discipline itself.
Every clinical decision in forensic psychiatry now carries potential legal scrutiny through Mental Health Tribunals, Hospital Managers’ hearings, Care Quality Commission inspections, or judicial review. The forensic psychiatrist must think simultaneously as clinician, legal actor, and rights arbiter. Questions that might appear medical—whether someone requires continued detention, whether treatment is appropriate, whether capacity exists for a particular decision—are fundamentally shaped by legal precedent rather than purely clinical consideration.
This legal architecture does not merely influence practice; it defines the very categories through which forensic psychiatrists must think. The concept of “nature or degree” sufficient to warrant detention, the “appropriate medical treatment test,” the distinction between “unsound mind” and capacity—these are legal constructs that have become the primary currency of forensic psychiatric discourse.
The reality of daily practice
An examination of how forensic psychiatrists actually spend their time reveals the extent of this transformation. The preparation of reports for Mental Health Tribunals and Hospital Managers’ appeals consumes substantial portions of working hours. Each hearing requires extensive preparation, with attendance often lasting two hours or considerably longer. These reports are not medical documents in any traditional sense but rather legal arguments constructed using medical terminology.
The forensic psychiatrist crafts arguments about why statutory criteria are met, anticipates legal challenges, and builds defensible paper trails. During tribunal hearings, the psychiatrist functions not as a treating physician but as an expert witness defending detention decisions against legal scrutiny. The medical opinion becomes subordinate to its legal defensibility. The core skill being exercised is the ability to translate psychiatric phenomena into legally actionable categories that will withstand adversarial examination.
Perhaps most tellingly, a significant portion of the forensic psychiatrist’s role involves explaining basic concepts of law and regulation to multidisciplinary teams. Nurses, occupational therapists, psychologists, and support workers all operate under the same legal frameworks but often with partial or misunderstood knowledge. The forensic psychiatrist must constantly clarify the legal implications of informal admission, the requirements for Section 17 leave, the relationship between capacity and consent to treatment under different sections of the Mental Health Act.
The instrumental role of medical knowledge
This analysis suggests that medical knowledge in forensic psychiatry has become instrumental rather than primary. The psychiatrist requires medical training to understand what they are interpreting, but the interpretation itself is fundamentally legal in nature. Courts and tribunals do not seek explanations of dopamine hypotheses or neurobiological mechanisms; they require determinations about whether someone knew their act was wrong, whether mental disorder substantially impaired responsibility, whether statutory criteria for detention are satisfied.
The expertise truly valued in forensic psychiatry is not diagnostic acumen or psychopharmacological sophistication but rather the ability to navigate statutory criteria, understand evolving case law, and maintain legally defensible documentation. A forensic psychiatrist who possesses moderate clinical skills but excellent tribunal report writing abilities will likely thrive more than one with the reverse skill set.
The paradox of psychiatric authority
This transformation creates a peculiar paradox. The legal framework depends entirely on psychiatric expertise to function—concepts like “abnormality of mental functioning” or “mental disorder” only have meaning because psychiatrists can recognise and describe them. Yet in exercising this expertise, psychiatrists find themselves functioning primarily as legal interpreters rather than medical practitioners.
The authority of forensic psychiatry derives from its medical foundation, but its daily practice is overwhelmingly legal-administrative. The discipline operates in a space where biological processes and legal categories must be reconciled, but the reconciliation occurs predominantly on legal rather than medical terms.
A sui generis discipline?
Perhaps the most accurate characterisation is that forensic psychiatry has evolved into something sui generis—neither properly medical nor properly legal, but a hybrid discipline that makes both lawyers and doctors slightly uncomfortable. It exists in the interstices between medicine and law, drawing authority from medicine while operating according to legal logic.
This hybrid nature is not necessarily problematic, but it does raise important questions about training, professional identity, and the future direction of the specialty. If forensic psychiatry is indeed more legal than medical in its contemporary form, should training programmes be restructured to reflect this reality? Should different competencies be prioritised in recruitment and professional development?
Implications for psychiatry’s core identity
This analysis of forensic psychiatry illuminates broader questions about psychiatry’s identity as a medical specialty. If one of psychiatry’s subspecialties can drift so far from traditional medical practice while remaining recognisably psychiatric, what does this suggest about the nature of psychiatry itself?
Psychiatry has always occupied an uncertain position between natural science and humanistic understanding, between biological intervention and social control. The example of forensic psychiatry suggests that this uncertainty is not a weakness to be resolved but perhaps a defining characteristic of the discipline. Psychiatry’s capacity to operate across different epistemological frameworks—biological, psychological, social, and legal—may be its unique contribution to medicine and society.
Conclusion
The proposition that forensic psychiatry has become more a legal than a medical discipline is intentionally provocative, designed to stimulate discussion about the nature and direction of the specialty. The evidence suggests that contemporary forensic psychiatric practice is dominated by legal-administrative tasks, that expertise is primarily valued for its legal rather than medical applications, and that the discipline’s conceptual framework is increasingly shaped by statutory and case law rather than medical science.
This transformation is neither inherently positive nor negative but rather reflects the complex reality of managing mental disorder within a rights-based legal framework. Acknowledging this reality might enable more honest discussions about training needs, resource allocation, and the future development of forensic psychiatry. It might also contribute to broader debates about psychiatry’s identity and its relationship with other disciplines and social institutions.
The question is not whether forensic psychiatry should be more medical or more legal, but rather how the specialty can best navigate its hybrid nature to serve both therapeutic and justice-oriented goals. Recognising that contemporary forensic psychiatry is primarily a legal-administrative discipline with medical foundations might be the first step toward a more coherent understanding of its role and potential.